Surgery-First Jaw Surgery: Who Can Skip Presurgical Orthodontics?
Selected patients can skip presurgical orthodontics only when the surgeon and orthodontist can create a stable immediate or transitional bite at surgery; if major alignment, leveling, decompensation, or arch coordinat... Good candidates usually have reasonably aligned arches, mild to moderate dental compensation, li...
Published byEdited with GPT-5.5Images generated with GPT Image 2
Selected patients can skip presurgical orthodontics only when the surgeon and orthodontist can create a stable immediate or transitional bite at surgery; if major alignment, leveling, decompensation, or arch coordinat...
Good candidates usually have reasonably aligned arches, mild to moderate dental compensation, limited transverse mismatch, and a realistic plan for postsurgical orthodontic finishing [1].
Red flags include severe crowding, severe dental compensation, unstable surgical setup, major transverse discrepancies, poor oral health or compliance concerns, and limited team experience with surgery first planning...
Surgery-First Orthognathic Surgery: Who Can Safely Skip Presurgical OrthodonticsSurgery-first orthognathic surgery depends on whether the care team can create a stable bite at the time of jaw repositioning.
AI Prompt
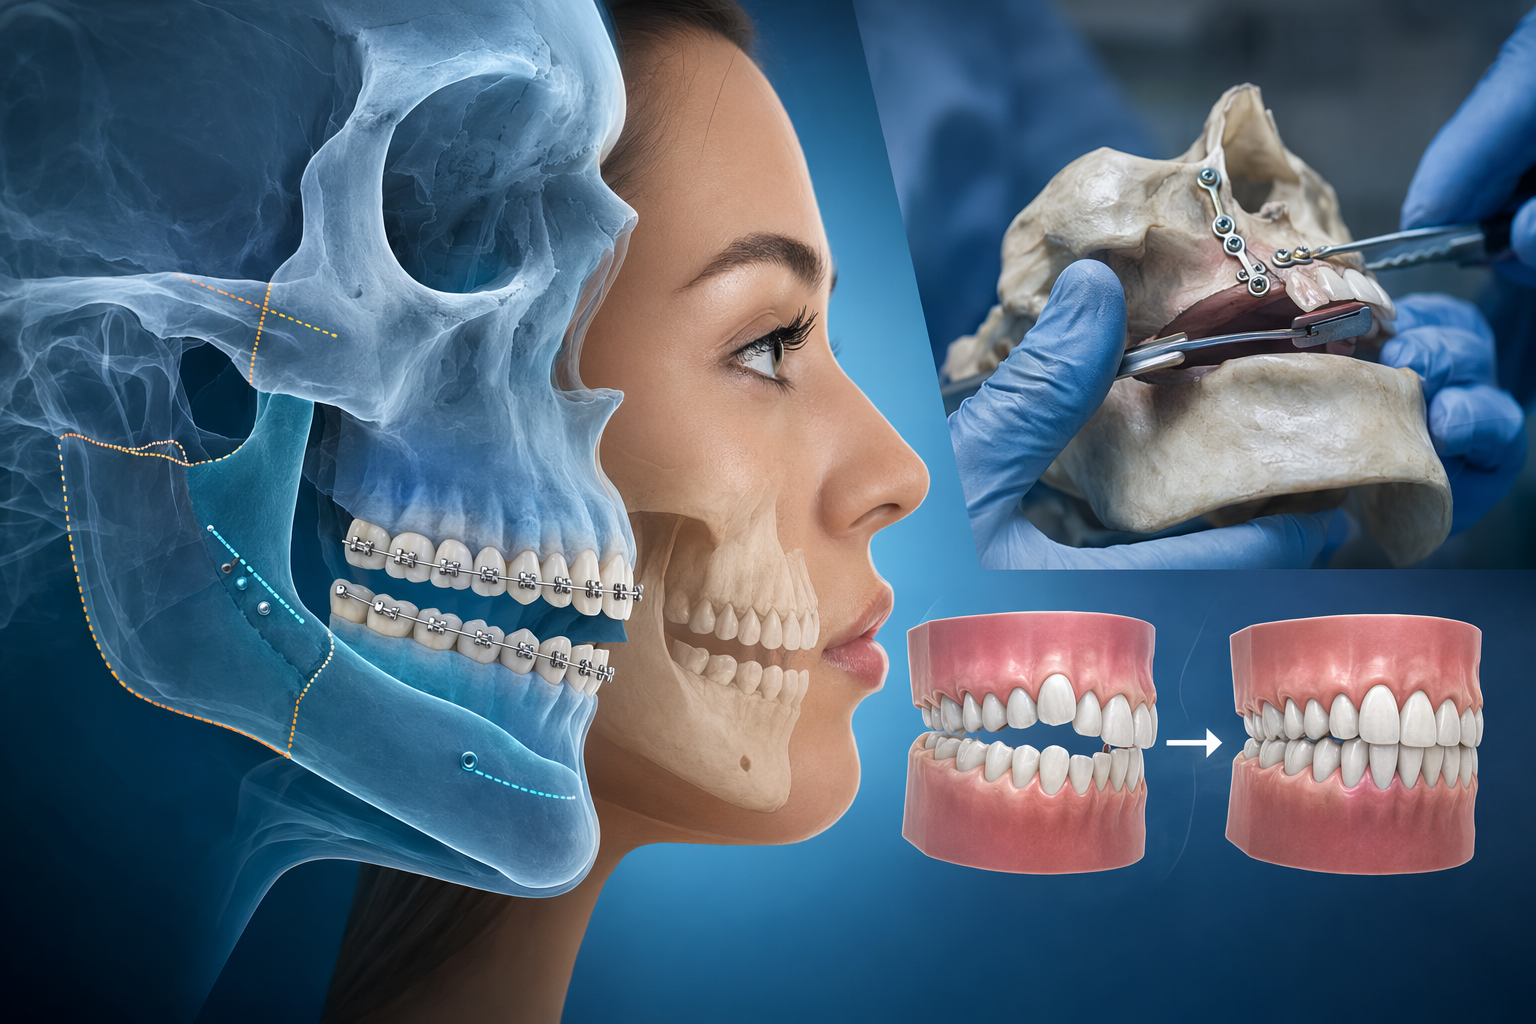
Create a landscape editorial hero image for this Studio Global article: Surgery-First Orthognathic Surgery: Who Can Safely Skip Presurgical Orthodontics?. Article summary: Selected patients can skip presurgical orthodontics only if jaw surgery can create a stable immediate postsurgical bite; if major alignment, leveling, decompensation, or arch coordination is needed first, the conventi.... Topic tags: orthognathic surgery, jaw surgery, orthodontics, maxillofacial surgery, oral surgery. Reference image context from search candidates: Reference image 1: visual subject "Before surgery, most people need to have orthodontic treatment to move and straighten the teeth. This lets the surgeon place the jaws in the correct position." source context "Jaw (Orthognathic) Surgery: Presurgical Orthodontics | UMass Memorial Health" Reference image 2: visual subject "A new process of employing bony corr
openai.com
Surgery-first orthognathic surgery can make treatment feel more direct, because jaw surgery happens before the long presurgical orthodontic phase used in the conventional sequence . But the approach is not simply a faster version of standard care. It is a case-selection strategy for patients whose teeth and jaw relationship allow the surgical team to position the jaws accurately before full orthodontic preparation .
What surgery-first treatment changes
Traditional orthognathic treatment is usually organized in three stages: presurgical orthodontics, jaw surgery, and postsurgical orthodontics . The surgery-first approach changes that order by moving jaw surgery to the beginning and shifting much of the orthodontic alignment, decompensation, and finishing into the postsurgical phase .
Studio Global AI
Continue your research
This page includes a source-backed answer you can continue inside Studio Global.
What is the short answer to "Surgery-First Jaw Surgery: Who Can Skip Presurgical Orthodontics?"?
Selected patients can skip presurgical orthodontics only when the surgeon and orthodontist can create a stable immediate or transitional bite at surgery; if major alignment, leveling, decompensation, or arch coordinat...
What are the key points to validate first?
Selected patients can skip presurgical orthodontics only when the surgeon and orthodontist can create a stable immediate or transitional bite at surgery; if major alignment, leveling, decompensation, or arch coordinat... Good candidates usually have reasonably aligned arches, mild to moderate dental compensation, limited transverse mismatch, and a realistic plan for postsurgical orthodontic finishing [1].
What should I do next in practice?
Red flags include severe crowding, severe dental compensation, unstable surgical setup, major transverse discrepancies, poor oral health or compliance concerns, and limited team experience with surgery first planning...
That sequence can be appealing because facial-profile changes may occur earlier, and some patients may avoid the temporary esthetic worsening that can happen during presurgical dental decompensation . The trade-off is that the teeth must still provide enough guidance for accurate surgery and a workable bite immediately afterward .
The real test: can surgery create a stable bite now?
The central question is whether the orthodontist and maxillofacial surgeon can establish a stable transitional occlusion at the time of surgery . In practical terms, the teeth do not need to be perfectly straight before surgery, but the upper and lower arches must fit well enough to guide jaw positioning and allow orthodontics to finish the bite afterward .
If substantial alignment, leveling, decompensation, extraction-space management, or arch coordination is needed before the jaws can be positioned reliably, presurgical orthodontics should not be skipped . Surgery-first works best when postsurgical orthodontics can predictably finish the case, not when orthodontics is required to make the surgery possible in the first place .
Best candidates for surgery-first orthognathic surgery
Surgery-first treatment is most suitable when the skeletal jaw discrepancy is the main problem and the dental problems are limited enough to manage after surgery . Favorable features include:
Reasonably aligned dental arches. Mild crowding, spacing, or rotations may be acceptable if they do not prevent a usable surgical and immediate postsurgical bite .
Mild-to-moderate dental compensation. Surgery-first is more realistic when incisor and molar positions do not require major decompensation before the jaw movement .
Minimal or manageable transverse discrepancy. A smaller upper-to-lower arch-width mismatch is more favorable; larger discrepancies need a clear correction plan .
A predictable immediate postsurgical occlusion. The team should be able to confirm a workable bite using clinical records, casts or digital scans, cephalometric analysis, and model or virtual surgical planning .
Selected skeletal Class II, Class III, asymmetry, or open-bite patterns. These patterns may be considered for surgery-first care, but only when dental compensation and arch incoordination are not severe .
Reliable patient participation. Because more orthodontic work occurs after surgery, the patient must be able to follow appointments, oral-hygiene instructions, elastic wear, and postsurgical guidance .
Red flags that argue against skipping presurgical orthodontics
Presurgical orthodontics should generally remain part of the plan when tooth position would compromise jaw positioning or make the immediate postsurgical bite unstable . Warning signs include:
Severe crowding, rotations, spacing, or blocked-out teeth that prevent a stable intraoperative or immediate postsurgical bite .
Severe dental compensation, such as markedly proclined or retroclined incisors, because compensation can mask the true skeletal discrepancy and affect surgical planning .
Large transverse discrepancies between the upper and lower arches unless they can be corrected surgically or managed through a defined staged plan .
An unstable or poorly defined occlusion during model surgery or virtual surgical planning .
A significant curve of Spee, vertical dental problems, occlusal cant, or arch asymmetry when those issues must be corrected before reliable jaw positioning is possible .
Treatment plans that depend on substantial extraction-space management. Selected extraction cases may still be possible, but a pure surgery-first sequence becomes more complex when space closure, incisor repositioning, or arch coordination must occur before surgery .
Oral-health, periodontal, hygiene, or anchorage concerns that could make the postsurgical orthodontic phase less predictable .
Poor expected compliance with elastics, appointments, hygiene, or postsurgical instructions .
Limited team experience with surgery-first protocols, because the approach depends heavily on precise orthodontic-surgical coordination .
Why dental decompensation often decides the answer
Many jaw-deformity patients have dental compensation, meaning the teeth tip or shift in ways that partly camouflage the skeletal discrepancy . In the conventional sequence, presurgical orthodontics is often used to decompensate those teeth before surgery so the jaws can be moved into the intended skeletal relationship .
Skipping that phase is reasonable only when the compensation is mild enough that it does not distort the surgical plan or leave difficult postsurgical mechanics . If compensation is severe, surgery-first can make jaw-movement planning less reliable and may leave the orthodontist with a harder finishing problem after surgery .
How candidacy should be evaluated
A surgery-first decision should be made jointly by the orthodontist and maxillofacial surgeon, not by patient preference alone . The evaluation typically tests whether the proposed jaw movement and bite are workable using clinical examination, cephalometric analysis, dental casts or digital scans, and model or virtual surgical planning .
A practical framework is simple: consider surgery-first when surgery can create a stable transitional bite and the remaining orthodontic work is realistic after surgery . Choose orthodontics-first when substantial tooth movement is needed before accurate jaw positioning is possible .
Bottom line
Surgery-first orthognathic surgery can be useful in the right case, but it is not a way to bypass orthodontic fundamentals . The best candidates are patients whose dental arches, skeletal discrepancy, oral health, compliance, and treatment team all support a stable surgical bite before full presurgical tooth preparation .